Gastrointestinal Tract - Mesentery Development: Difference between revisions
(Created page with "{{Header}} ==Introduction== thumb|midgut herniation The adult gastrointestinal tract (GIT) is attached along its length between the stomach and anus by a...") |
mNo edit summary |
||
| Line 17: | Line 17: | ||
| | | | ||
* '''The development of the dorsal mesentery in human embryos and fetuses'''{{#pmid:30142441|PMID30142441}} "The vertebrate intestine has a continuous dorsal mesentery between pharynx and anus that facilitates intestinal mobility. Based on width and fate the dorsal mesentery can be subdivided into that of the caudal foregut, midgut, and hindgut. The dorsal mesentery of stomach and duodenum is wide and topographically complex due to strong and asymmetric growth of the stomach. The associated formation of the lesser sac partitions the dorsal mesentery into the right-sided "caval fold" that serves as conduit for the inferior caval vein and the left-sided mesogastrium. The thin dorsal mesentery of the midgut originates between the base of the superior and inferior mesenteric arteries, and follows the transient increase in intestinal growth that results in small-intestinal looping, intestinal herniation and, subsequently, return. The following fixation of a large portion of the abdominal dorsal mesentery to the dorsal peritoneal wall by adhesion and fusion is only seen in primates and is often incomplete. Adhesion and fusion of mesothelial surfaces in the lesser pelvis results in the formation of the "mesorectum". | * '''The development of the dorsal mesentery in human embryos and fetuses'''{{#pmid:30142441|PMID30142441}} "The vertebrate intestine has a continuous dorsal mesentery between pharynx and anus that facilitates intestinal mobility. Based on width and fate the dorsal mesentery can be subdivided into that of the caudal foregut, midgut, and hindgut. The dorsal mesentery of stomach and duodenum is wide and topographically complex due to strong and asymmetric growth of the stomach. The associated formation of the lesser sac partitions the dorsal mesentery into the right-sided "caval fold" that serves as conduit for the inferior caval vein and the left-sided mesogastrium. The thin dorsal mesentery of the midgut originates between the base of the superior and inferior mesenteric arteries, and follows the transient increase in intestinal growth that results in small-intestinal looping, intestinal herniation and, subsequently, return. The following fixation of a large portion of the abdominal dorsal mesentery to the dorsal peritoneal wall by adhesion and fusion is only seen in primates and is often incomplete. Adhesion and fusion of mesothelial surfaces in the lesser pelvis results in the formation of the "mesorectum". | ||
* '''Digestive Tract in Human Embryos Between Carnegie Stages 11 and 13'''{{#pmid:26995337|PMID26995337}} "We selected 37 human embryos at Carnegie Stage (CS) {{CS11}}-{{CS13}} (28-33 days after fertilization) and three-dimensionally analyzed the morphology and positioning of the digestive tract and derived primordia in all samples, using images reconstructed from histological serial sections. The digestive tract was initially formed by a narrowing of the yolk sac, and then several derived primordia such as the pharynx, lung, stomach, liver, and dorsal pancreas primordia differentiated during CS12 (21-29 somites) and CS13 (≥ 30 somites). The differentiation of four pairs of pharyngeal pouches was complete in all CS13 embryos. The respiratory primordium was recognized in ≥ 26-somite embryos and it flattened and then branched at CS13. The trachea formed and then elongated in ≥ 35-somite embryos. The stomach adopted a spindle shape in all ≥ 34-somite embryos, and the liver bud was recognized in ≥ 27-somite embryos. The dorsal pancreas appeared as definitive buddings in all but three CS13 embryos, and around these buddings, the small intestine bent in ≥ 33-somite embryos. In ≥ 35-somite embryos, the small intestine rotated around the cranial-caudal axis and had begun to form a primitive intestinal loop, which led to umbilical herniation." | * '''Digestive Tract in Human Embryos Between Carnegie Stages 11 and 13'''{{#pmid:26995337|PMID26995337}} "We selected 37 human embryos at Carnegie Stage (CS) {{CS11}}-{{CS13}} (28-33 days after fertilization) and three-dimensionally analyzed the morphology and positioning of the digestive tract and derived primordia in all samples, using images reconstructed from histological serial sections. The digestive tract was initially formed by a narrowing of the yolk sac, and then several derived primordia such as the pharynx, lung, stomach, liver, and dorsal pancreas primordia differentiated during CS12 (21-29 somites) and CS13 (≥ 30 somites). The differentiation of four pairs of pharyngeal pouches was complete in all CS13 embryos. The respiratory primordium was recognized in ≥ 26-somite embryos and it flattened and then branched at CS13. The trachea formed and then elongated in ≥ 35-somite embryos. The stomach adopted a spindle shape in all ≥ 34-somite embryos, and the liver bud was recognized in ≥ 27-somite embryos. The dorsal pancreas appeared as definitive buddings in all but three CS13 embryos, and around these buddings, the small intestine bent in ≥ 33-somite embryos. In ≥ 35-somite embryos, the small intestine rotated around the cranial-caudal axis and had begun to form a primitive intestinal loop, which led to umbilical herniation." | ||
| Line 35: | Line 33: | ||
|- | |- | ||
| | | | ||
* '''Growth of the colon and rectum throughout gestation: evaluation with fetal MRI'''{{#pmid:29531795|PMID29531795}} "Congenital abnormalities of the gastrointestinal tract are increasingly being evaluated by prenatal magnetic resonance imaging (MRI). However, there is a paucity of reports describing the normal quantitative development of the fetal colon and rectum on MRI. This study provides normal ranges of the prenatal colon and rectum as a function of gestational age. They may serve as reference values when interpreting fetal MRI." | |||
* '''Review - How to make an intestine'''{{#pmid:24496613|PMID24496613}} With the high prevalence of gastrointestinal disorders, there is great interest in establishing in vitro models of human intestinal disease and in developing drug-screening platforms that more accurately represent the complex physiology of the intestine. We will review how recent advances in developmental and stem cell biology have made it possible to generate complex, three-dimensional, human intestinal tissues in vitro through directed differentiation of human pluripotent stem cells. | * '''Review - How to make an intestine'''{{#pmid:24496613|PMID24496613}} With the high prevalence of gastrointestinal disorders, there is great interest in establishing in vitro models of human intestinal disease and in developing drug-screening platforms that more accurately represent the complex physiology of the intestine. We will review how recent advances in developmental and stem cell biology have made it possible to generate complex, three-dimensional, human intestinal tissues in vitro through directed differentiation of human pluripotent stem cells. | ||
Revision as of 15:19, 22 October 2018
Embryology - 27 Oct 2026    Expand to Translate |
|---|
| Google Translate - select your language from the list shown below (this will open a new external page) |
|
العربية | català | 中文 | 中國傳統的 | français | Deutsche | עִברִית | हिंदी | bahasa Indonesia | italiano | 日本語 | 한국어 | မြန်မာ | Pilipino | Polskie | português | ਪੰਜਾਬੀ ਦੇ | Română | русский | Español | Swahili | Svensk | ไทย | Türkçe | اردو | ייִדיש | Tiếng Việt These external translations are automated and may not be accurate. (More? About Translations) |
Introduction

The adult gastrointestinal tract (GIT) is attached along its length between the stomach and anus by a dorsal mesentery.
Some Recent Findings

|
| More recent papers |
|---|
  This table allows an automated computer search of the external PubMed database using the listed "Search term" text link.
More? References | Discussion Page | Journal Searches | 2019 References | 2020 References Search term: Mesentery Embryology <pubmed limit=5>Mesentery Embryology</pubmed> |
| Older papers |
|---|
|
Small Intestine
Intestinal Functions
Small Intestine
- absorption of nutrients and minerals found in food
- Duodenum -principal site for iron absorption
Colon
- absorbs fluid, water and salts, from solid wastes
Embryonic Development
Week 4
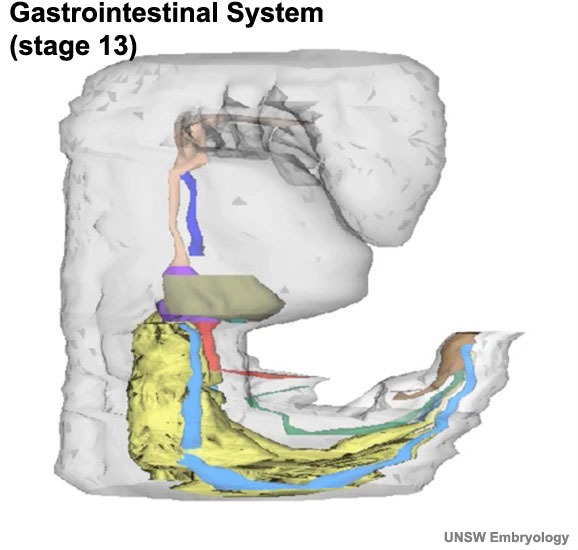
|
Colour code:
|
Week 7

Human embryo small intestine secondary loops (week 7 to 8).[6]
Week 8

|
|


Late embryonic small intestine commencing at the duodenum, continuing as ventrally herniated and returning to join the colon.
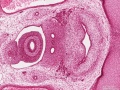
rectum and bladder
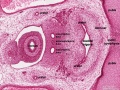
rectum and bladder labeled
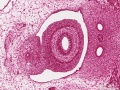
rectum
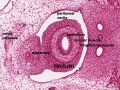
rectum labeled


Small intestine tertiary loops week 8.[6]
- Links: Carnegie stage 22 | Week 8
Rotation
A recent 3 dimensional study[6] has suggested a modified “en-bloc rotation” of the small intestine, compared the the earlier simplified description of 270 degree rotation.
Fetal Intestine Length

|

|
| Fetal small Intestine length growth | Fetal Large Intestine length growth |

Data fromCite error: Invalid <ref> tag; name cannot be a simple integer. Use a descriptive title
Small Intestine Length
Small intestine growth in length is initially linear (first half pregnancy to 32 cm CRL), followed by rapid growth in the last 15 weeks doubling the overall length. Growth continues postnatally but after 1 year slows again to a linear increase to adulthood.[9]
| Age (weeks gestational age) | Average Length (cm) |
| 20 | 125 |
| 30 | 200 |
| term | 275 |
| 1 year postnatal | 380 |
| 5 years | 450 |
| 10 years | 500 |
| 20 years | 575 |
Table data based upon 8 published reports of necropsy measurement of 1010 guts.[9]
Hindgut
Anatomically the distal third of the transverse colon and the splenic flexure, the descending colon, sigmoid colon and rectum. The developmental timing of the anus and rectum formation[10] in human embryos of the Carnegie Collection has been previously carried out (1974). A more recent study[11] has also been made of the Kyoto Collection embryos.
There has been some recent controversy over the "anal membrane" formation.
A recent study hindgut and anorectum development in human embryos shows that WNT5a is active in this region prior to anus formation, when it is down-regulated.[12]
Other studies - [13][14][15][16][17] (rat)
Abnormalities
Short Bowel Syndrome
Short bowel syndrome (SBS) results typically due to developmental abnormalities, extensive intestinal resection during the neonatal period, or necrotising enterolitis.[18]
- reduces gut function for digestion and absorption of nutrients (intestinal failure).
- Links: PubMed Health | Better Health
Molecular Factors
References
- ↑ Xu K, Wu X, Shapiro E, Huang H, Zhang L, Hickling D, Deng Y, Lee P, Li J, Lepor H & Grishina I. (2012). Bmp7 functions via a polarity mechanism to promote cloacal septation. PLoS ONE , 7, e29372. PMID: 22253716 DOI.
- ↑ Hikspoors JPJM, Kruepunga N, Mommen GMC, Peeters JPWU, Hülsman CJM, Eleonore Köhler S & Lamers WH. (2018). The development of the dorsal mesentery in human embryos and fetuses. Semin. Cell Dev. Biol. , , . PMID: 30142441 DOI.
- ↑ Ueno S, Yamada S, Uwabe C, Männer J, Shiraki N & Takakuwa T. (2016). The Digestive Tract and Derived Primordia Differentiate by Following a Precise Timeline in Human Embryos Between Carnegie Stages 11 and 13. Anat Rec (Hoboken) , 299, 439-49. PMID: 26995337 DOI.
- ↑ Ben-Nun MS, Ben-Shlush A & Raviv Zilka L. (2018). Growth of the colon and rectum throughout gestation: evaluation with fetal MRI. Acta Radiol Open , 7, 2058460118761206. PMID: 29531795 DOI.
- ↑ Wells JM & Spence JR. (2014). How to make an intestine. Development , 141, 752-60. PMID: 24496613 DOI.
- ↑ 6.0 6.1 6.2 Soffers JH, Hikspoors JP, Mekonen HK, Koehler SE & Lamers WH. (2015). The growth pattern of the human intestine and its mesentery. BMC Dev. Biol. , 15, 31. PMID: 26297675 DOI.
- ↑ FitzSimmons J, Chinn A & Shepard TH. (1988). Normal length of the human fetal gastrointestinal tract. Pediatr Pathol , 8, 633-41. PMID: 3244599
- ↑ Archie JG, Collins JS & Lebel RR. (2006). Quantitative standards for fetal and neonatal autopsy. Am. J. Clin. Pathol. , 126, 256-65. PMID: 16891202 DOI.
- ↑ 9.0 9.1 Weaver LT, Austin S & Cole TJ. (1991). Small intestinal length: a factor essential for gut adaptation. Gut , 32, 1321-3. PMID: 1752463
- ↑ de Vries PA. and Friedland GW. The staged sequential development of the anus and rectum in human embryos and fetuses. (1974) J. Pediatr. Surg., 9(5): 755-69 PMID 4424274
- ↑ Hashimoto R. (2013). Development of the human tail bud and splanchnic mesenchyme. Congenit Anom (Kyoto) , 53, 27-33. PMID: 23480355 DOI.
- ↑ Li FF, Zhang T, Bai YZ, Yuan ZW & Wang WL. (2011). Spatiotemporal expression of Wnt5a during the development of the hindgut and anorectum in human embryos. Int J Colorectal Dis , 26, 983-8. PMID: 21431850 DOI.
- ↑ van der Putte SC. (2009). The development of the human anorectum. Anat Rec (Hoboken) , 292, 951-4. PMID: 19496155 DOI.
- ↑ Kromer P. (1999). Further study of the urorectal septum in staged human embryos. Folia Morphol. (Warsz) , 58, 53-63. PMID: 10504783
- ↑ Nievelstein RA, van der Werff JF, Verbeek FJ, Valk J & Vermeij-Keers C. (1998). Normal and abnormal embryonic development of the anorectum in human embryos. Teratology , 57, 70-8. PMID: 9562679 <70::AID-TERA5>3.0.CO;2-A DOI.
- ↑ Kromer P. (1996). Development of the urorectal septum and differentiation of the urogenital sinus in human embryos of stages 13 to 19. Folia Morphol. (Warsz) , 55, 362-3. PMID: 9243909
- ↑ Kluth D, Fiegel HC & Metzger R. (2011). Embryology of the hindgut. Semin. Pediatr. Surg. , 20, 152-60. PMID: 21708335 DOI.
- ↑ Davì G, Pinto A, Palumbo MG, Gallo V, Mazza A & Strano A. (1985). Dipyridamole and aspirin in arteriosclerosis obliterans of the lower limbs. Adv. Prostaglandin Thromboxane Leukot. Res. , 13, 271-5. PMID: 3159212
Reviews
Wells JM & Spence JR. (2014). How to make an intestine. Development , 141, 752-60. PMID: 24496613 DOI.
Noah TK, Donahue B & Shroyer NF. (2011). Intestinal development and differentiation. Exp. Cell Res. , 317, 2702-10. PMID: 21978911 DOI.
Burns AJ, Roberts RR, Bornstein JC & Young HM. (2009). Development of the enteric nervous system and its role in intestinal motility during fetal and early postnatal stages. Semin. Pediatr. Surg. , 18, 196-205. PMID: 19782301 DOI.
Articles
Cho BH, Kim JH, Jin ZW, Wilting J, Rodríguez-Vázquez JF & Murakami G. (2018). Topographical anatomy of the intestines during in utero physiological herniation. Clin Anat , 31, 583-592. PMID: 29044646 DOI.
Soffers JH, Hikspoors JP, Mekonen HK, Koehler SE & Lamers WH. (2015). The growth pattern of the human intestine and its mesentery. BMC Dev. Biol. , 15, 31. PMID: 26297675 DOI.
Ueda Y, Yamada S, Uwabe C, Kose K & Takakuwa T. (2016). Intestinal Rotation and Physiological Umbilical Herniation During the Embryonic Period. Anat Rec (Hoboken) , 299, 197-206. PMID: 26599074 DOI.
Kim TH, Kim BM, Mao J, Rowan S & Shivdasani RA. (2011). Endodermal Hedgehog signals modulate Notch pathway activity in the developing digestive tract mesenchyme. Development , 138, 3225-33. PMID: 21750033 DOI.
Kim WK, Kim H, Ahn DH, Kim MH & Park HW. (2003). Timetable for intestinal rotation in staged human embryos and fetuses. Birth Defects Res. Part A Clin. Mol. Teratol. , 67, 941-5. PMID: 14745932 DOI.
Search Pubmed
Search Bookshelf Mesentery Development
Search Pubmed Now: Mesentery Embryology | Mesentery Development
Additional Images
Historic Images
| Historic Disclaimer - information about historic embryology pages |
|---|
|
Frazer JE. and Robbins RH. On the factors concerned in causing rotation of the intestine in man. (1915) J Anat. 50(1): 75-110. PMID 17233053
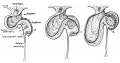
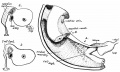
- Intestine Development
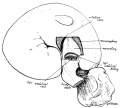
1 embryo 5 mm
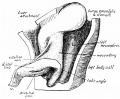
2 embryo 8 mm
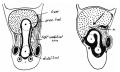
3 vitello-umbilical anastomosis
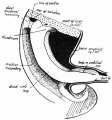
4 proximal limb of loop
5 curve of the duodenum
6 embryo 7.5 mm
7 mesentery
8 embryo 35 mm
9 embryo 28 mm
10 embryo 35 mm
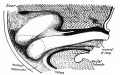
11 embryo 22 mm
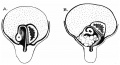
12 liver lobes and bowel
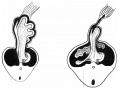
13 returning proximal limb of loop
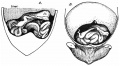
14 embryo 45 mm
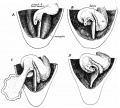
15 before and after bowel return

16 fetus 63 mm
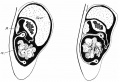
17 left abdomen
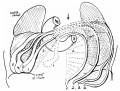
18 colon at different periods


External Links
External Links Notice - The dynamic nature of the internet may mean that some of these listed links may no longer function. If the link no longer works search the web with the link text or name. Links to any external commercial sites are provided for information purposes only and should never be considered an endorsement. UNSW Embryology is provided as an educational resource with no clinical information or commercial affiliation.
- NIH PubMed Health Short Bowel Syndrome
Glossary Links
- Glossary: A | B | C | D | E | F | G | H | I | J | K | L | M | N | O | P | Q | R | S | T | U | V | W | X | Y | Z | Numbers | Symbols | Term Link
Cite this page: Hill, M.A. (2026, October 27) Embryology Gastrointestinal Tract - Mesentery Development. Retrieved from https://embryology.med.unsw.edu.au/embryology/index.php/Gastrointestinal_Tract_-_Mesentery_Development
- © Dr Mark Hill 2026, UNSW Embryology ISBN: 978 0 7334 2609 4 - UNSW CRICOS Provider Code No. 00098G
